Meet Professor Jose Caceres and his Muppet
Dear friends, welcome to Caceres’ Corner. The objective of this post is to remember basic principles of chest imaging, with the emphasis on conventional radiography. Interpreting a chest radiograph is becoming a lost art and I would like to slow this tendency by reviewing the current approach to chest x-ray.
Nowadays, the initial question when facing a chest radiograph should be: “is there any abnormality present? And, if so, should we do any additional examination?” (CT in the great majority of cases).
With this approach in mind, let’s start with a sample case: 62 year old male with liver cirrhosis and upper gastrointestinal bleeding. No other symptoms. History of pulmonary tuberculosis 20 years ago.
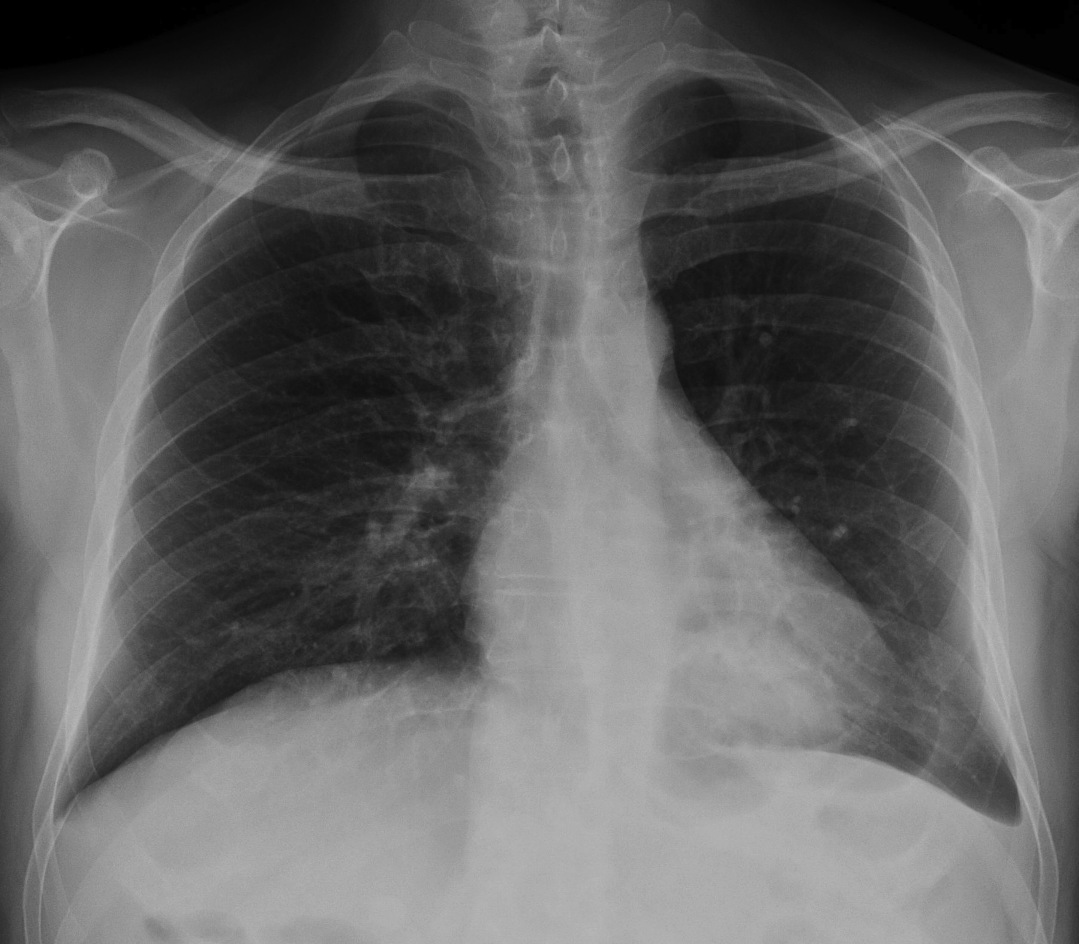
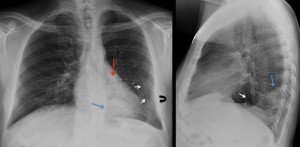
62 year old male with liver cirrhosis and upper gastrointestinal bleeding (PA view)
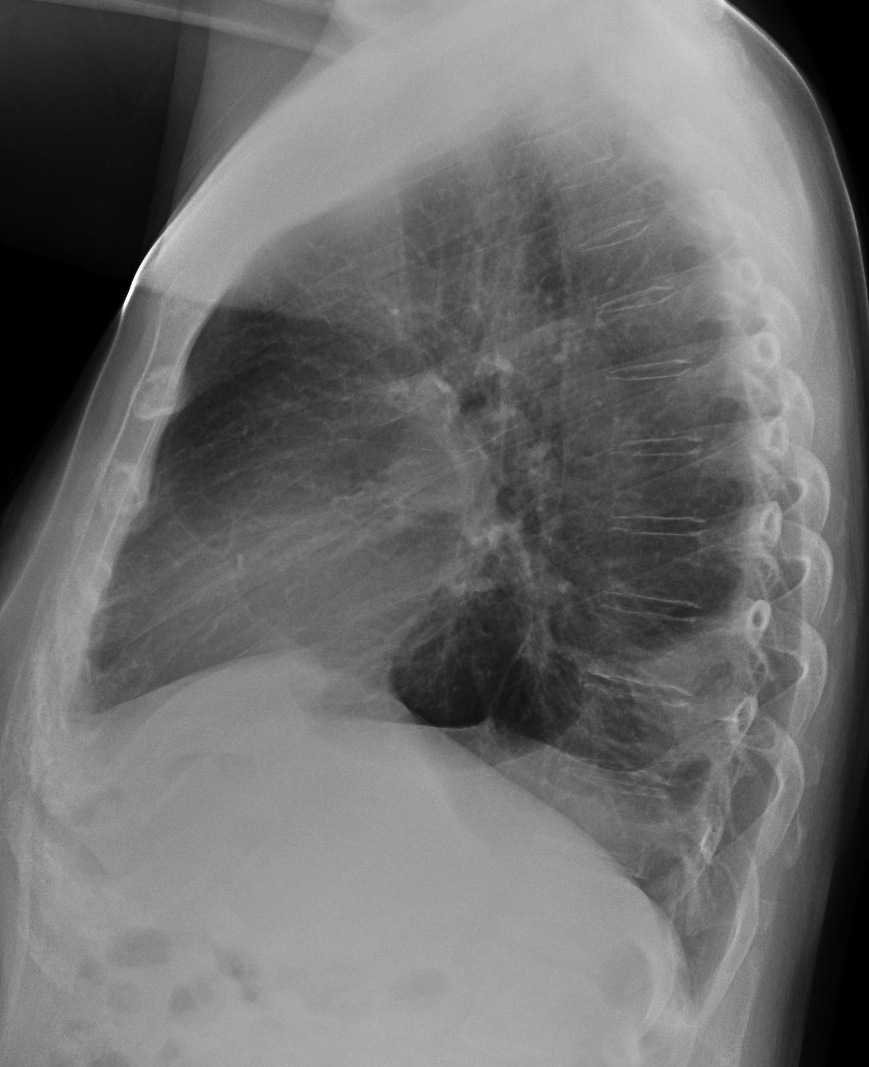
62 year old male (lateral view)
The most likely diagnosis would be:
- Blood aspiration
- Loculated pleural fluid
- Carcinoma of the lung
- None of the above
I will be back with the solution in 1-2 weeks depending upon the number of answers posted. My muppet and I will be delighted to answer all your questions and comments (muppet will be in charge of the difficult ones).
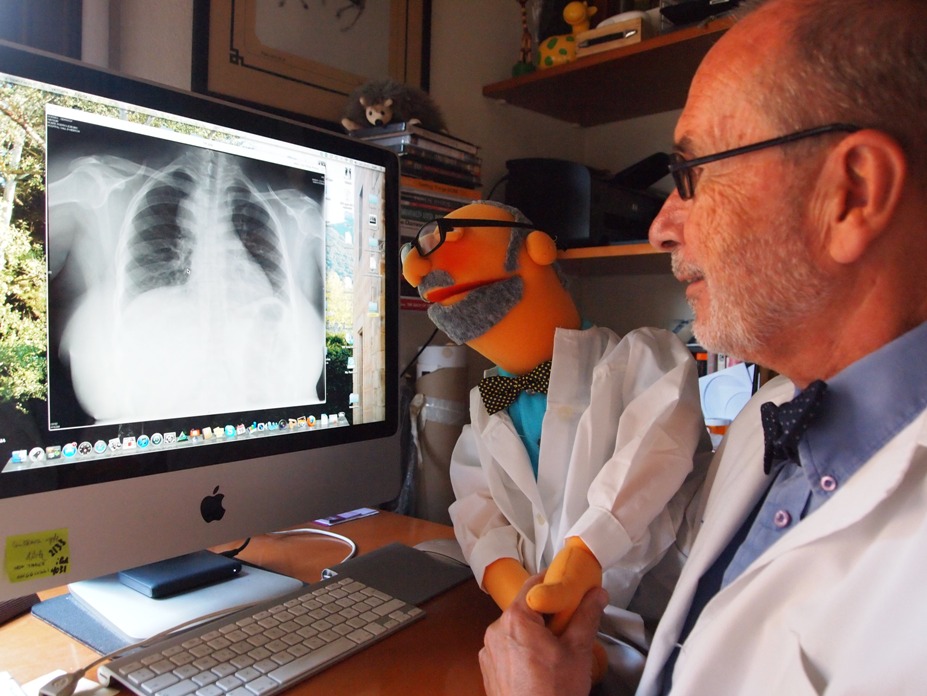
Muppet guides Prof. Caceres through the options
Click here for the answer to Case #1!
Answer to Case #1
I find this case very interesting because it illustrates the basic principles of interpreting a chest radiograph.
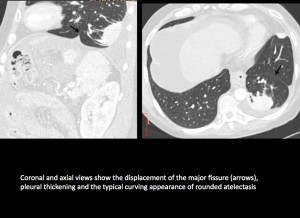
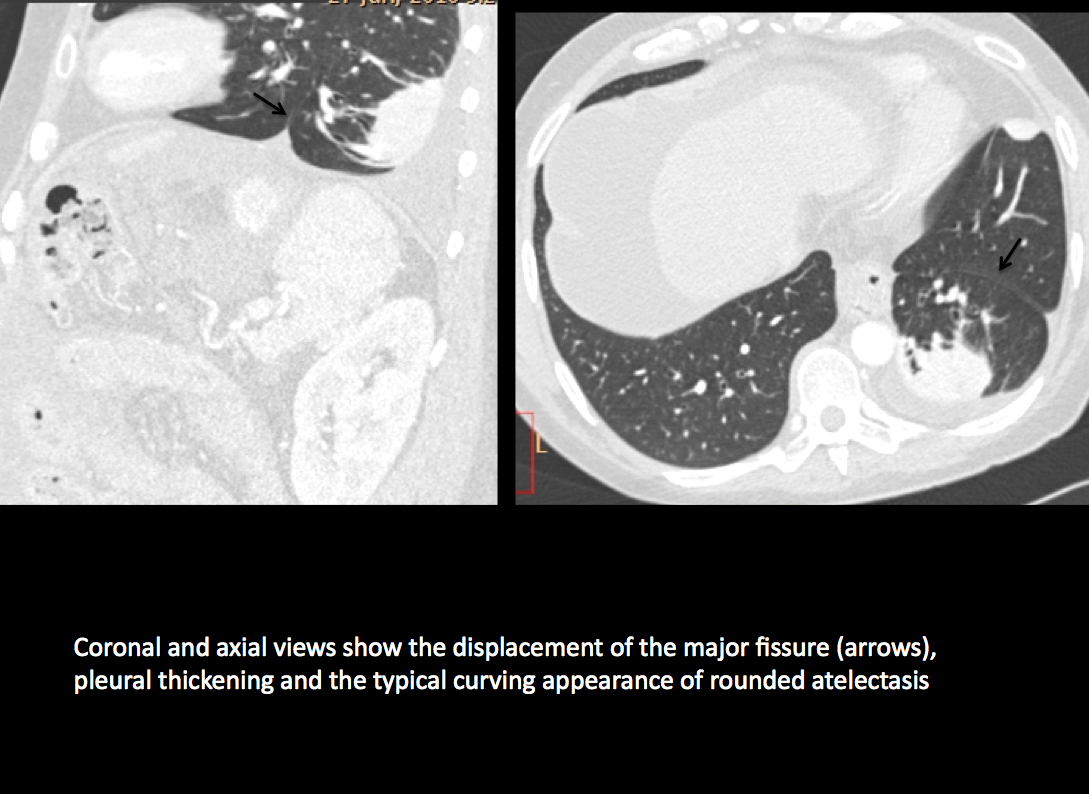
Coronal and axial views show the displacement of the major fissure (arrows), pleural thickening and the typical curving appearance of rounded atelectasis
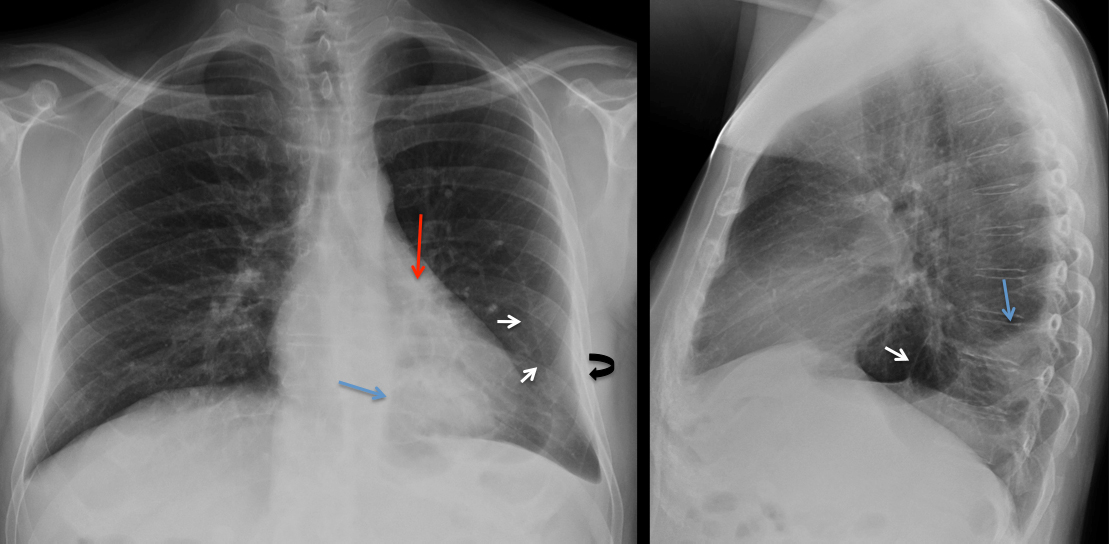
What we see is pleural thickening (curved arrow), blunting of the costophrenic angle and a peripheral rounded lesion (blue arrow). It is slightly ill-defined, which favours a pulmonary origin (option 3) over loculated pleural fluid (option 2). Aspiration of blood (option 1) should occur in the right side and gives an air-space pattern.
The right answer is option 4. There is a thing called “satisfaction of search” (Muppet calls it “satisfaction of sex”), meaning that, even though we see the abnormality, we have to look elsewhere. And, when we look, we discover that the left hilum is markedly descended (red arrow) and the major fissure is displaced medially and downward (white arrows), both findings indicating marked loss of volume of left lower lobe.
When we put together a peripheral rounded lesion, loss of volume and pleural thickening, rounded atelectasis immediately comes to mind and it is the correct diagnosis in this case. The typical findings of this condition are confirmed with CT (Fig 3).
Teaching points:
1. In the PA chest radiograph always look at the fissures, costophrenic angles and hila (size, density and position).
2. Rounded atelectasis anchors in thickened pleura. Do not suggest the diagnosis if the pleura looks normal.